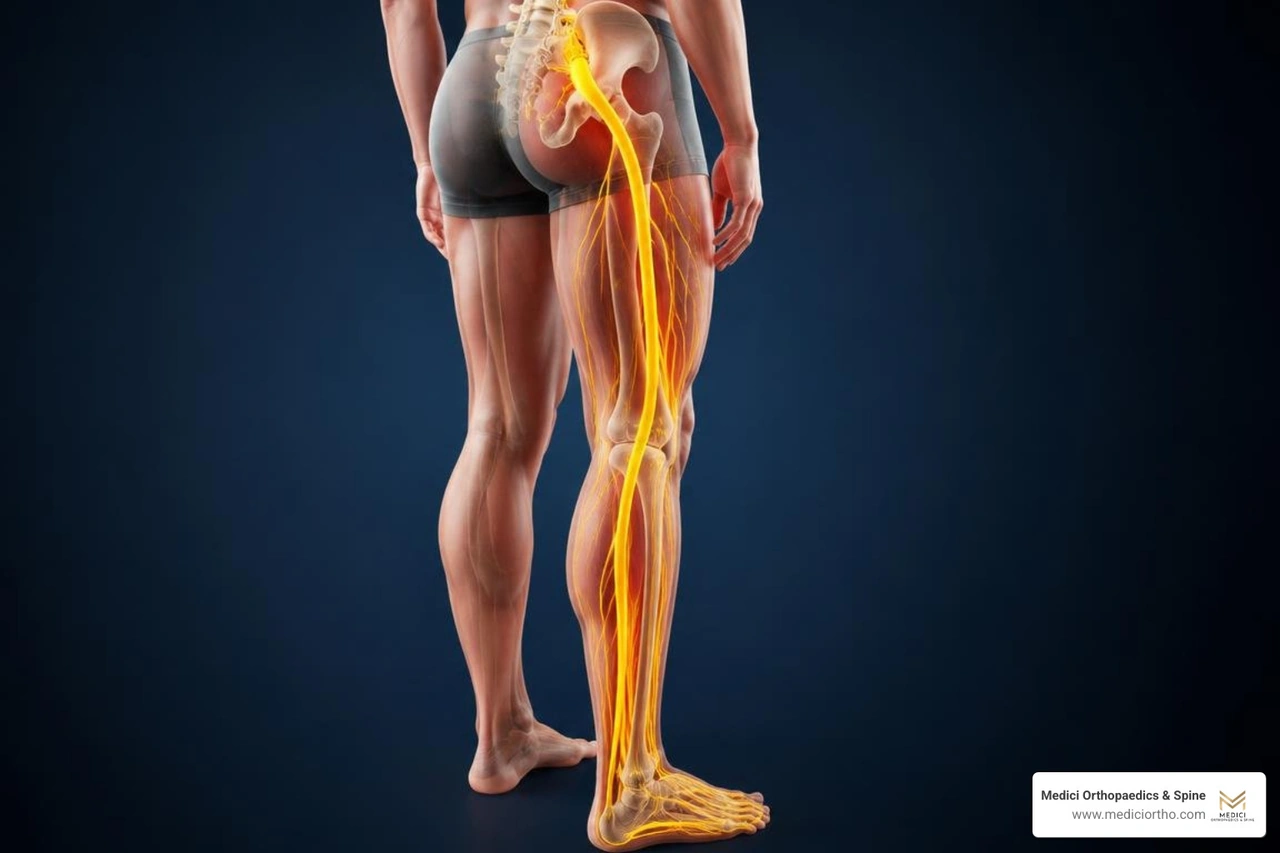
Calf and foot numbness can come from temporary pressure on a nerve, but recurring or lasting numbness may point to sciatica, peripheral neuropathy, diabetes, poor circulation, or an exercise-related injury. The pattern offers useful clues: numbness on one side that travels from the low back down the leg often suggests a pinched nerve, while gradual numbness in both feet may suggest neuropathy. Cold, pale feet or calf cramping with walking can signal reduced blood flow.
Seek urgent care for sudden numbness with weakness or foot drop, loss of bladder or bowel control, severe swelling, or a foot that becomes cold, pale, blue, or very painful. Otherwise, schedule an evaluation if symptoms persist, worsen, affect balance, or occur with diabetes, back pain, or wounds that are slow to heal.
I am Sonny Dosanjh, M.D., a board-certified Physical Medicine & Rehabilitation physician with fellowship training in multidisciplinary pain management. At Medici Orthopaedics & Spine, I evaluate calf and foot numbness related to spine conditions, sports injuries, neuropathy, and nerve pain to help patients find the least invasive path back to safe movement.

Calf and foot numbness terms explained:
When sensation fades in your lower leg or foot, your body is sounding an early alarm. Sensory signals rely on an uninterrupted pathway of healthy nerves powered by steady blood flow. When that pathway is disturbed by mechanical compression, systemic inflammation, or reduced circulation, the brain stops receiving accurate sensory input. According to a Medical News Today overview of lower extremity numbness, common drivers range from simple positional nerve pressure to complex metabolic and vascular conditions.
The nervous system functions like an intricate electrical grid. When a spinal disc herniates or spinal stenosis narrows the spinal canal in your lower back, it can pinch the nerve roots feeding into the sciatic nerve. This condition, known as lumbar radiculopathy, produces numbness, tingling, or sharp pain along distinct dermatomal lines extending through the buttock, hamstring, calf, and into the foot.
Further down the leg, peripheral nerves encounter other narrow passageways. The common peroneal nerve wraps around the neck of the fibula near the knee and can become trapped by tight connective tissue, braces, or habitual leg crossing. Similarly, the tibial nerve passes behind the bony inner ankle inside a tight fibro-osseous space. Compression here results in tarsal tunnel syndrome, which causes localized burning, numbness, and aching along the sole and heel of the foot.
Over 20 million Americans live with some form of peripheral neuropathy. Rather than isolated mechanical pinching, peripheral neuropathy involves systemic damage to microscopic nerve fibers. High blood sugar is the single most common culprit: roughly 50% of people with diabetes eventually develop diabetic neuropathy. Prolonged hyperglycemia creates oxidative stress and damages the tiny microvascular capillaries feeding your nerves, causing them to degenerate from the longest distal ends upward in a classic "stocking-glove" distribution.
Other systemic triggers can damage peripheral nerve axons:
Your nerves require constant oxygen and glucose from arterial blood to transmit sensory data. Peripheral artery disease (PAD) occurs when atherosclerosis narrows the arteries supplying the lower limbs. PAD affects approximately 8.5 million U.S. adults over age 40 and over 113 million people globally. Up to 4 in 10 individuals with PAD exhibit no obvious symptoms during early stages.
As arterial plaque builds up, blood flow decreases significantly during activity, causing cramping, heaviness, and numbness known as intermittent claudication. If venous valves fail instead, venous insufficiency causes pooled deoxygenated blood, swelling, and tingling sensations in the calves. In acute situations, a deep vein thrombosis (DVT) or sudden arterial blockage can severely compromise lower leg tissue, demanding immediate emergency care.
It is not uncommon for athletes and runners to experience calf or foot numbness midway through a workout. High-impact running increases blood flow to working muscles, causing them to expand. Within the lower leg, muscles are divided into rigid compartments encased by inelastic fascia. In chronic exertional compartment syndrome (CECS), muscle swelling during workouts raises pressure inside these compartments, compressing local blood vessels and nerves until the activity stops.
Other exercise-related causes include:
Distinguishing between spinal nerve compression, peripheral neuropathy, and vascular insufficiency is essential for effective treatment. Clinicians look closely at symmetry, triggers, and physical signs to uncover the root source, as detailed in this differential guide on lower extremity numbness.
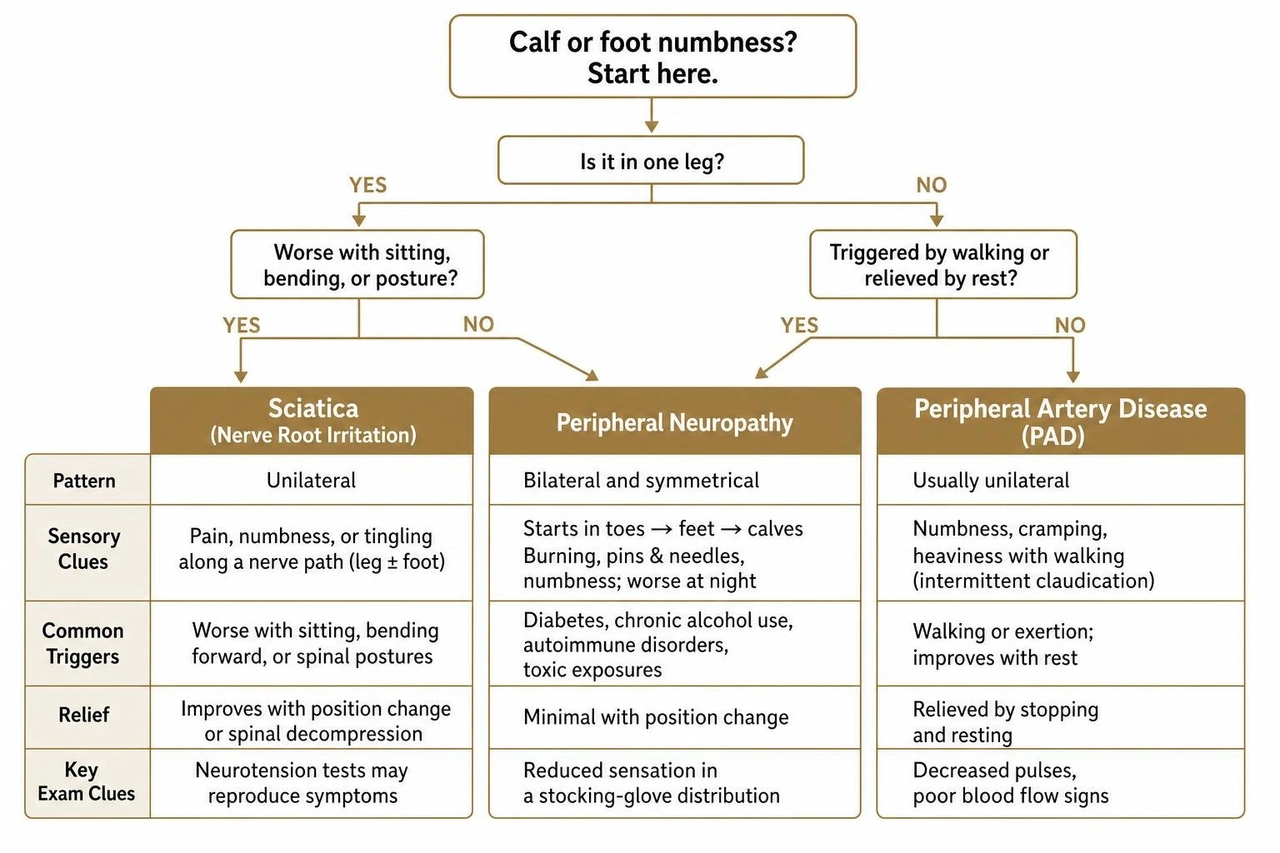
The specific sensations and their timing provide critical diagnostic clues:
The following comparison illustrates key distinctions between these conditions:
| Feature | Lumbar Radiculopathy (Sciatica) | Peripheral Neuropathy | Peripheral Artery Disease (PAD) |
|---|---|---|---|
| Typical Pattern | Unilateral; follows a single nerve pathway | Bilateral; symmetrical stocking pattern | Bilateral or unilateral; calf-dominant |
| Primary Sensation | Sharp, shooting pain with tingling | "Pins and needles," burning, cotton-ball feel | Cramping, tight ache, heavy fatigue |
| Aggravating Factor | Prolonged sitting, coughing, spine flexion | Nighttime, resting in bed | Walking, climbing stairs, exertion |
| Relieving Factor | Position changes, walking, lying down | Gentle movement, cool or warm compresses | Stopping activity and resting for 2–5 minutes |
| Skin / Foot Signs | Normal skin color and hair growth | Reduced vibration sense, dry skin | Pale/cold skin, loss of leg hair, weak pulse |
While many cases develop gradually, certain lower leg symptoms represent medical emergencies requiring immediate hospital evaluation:
A definitive diagnosis begins with a hands-on physical and neurological examination. We assess motor strength, deep tendon reflexes at the knee and Achilles tendon, and evaluate sensory thresholds using specialized tools.
Sensory testing includes Semmes-Weinstein monofilament examinations to evaluate protective sensation on the plantar surface, alongside 128-Hz tuning fork vibration testing. To check circulation, we palpate the dorsalis pedis and posterior tibial pulses and measure the Ankle-Brachial Index (ABI)—comparing systolic blood pressure in the ankle to that in the arm. An ABI score below 0.90 indicates significant arterial narrowing.
When physical exams point to deeper nerve or structural pathology, advanced testing helps pinpoint the problem:
Finding lasting relief from lower leg numbness requires addressing the root cause rather than just masking symptoms. A patient-centered strategy combines clinical interventions with home care, drawing on our specialized approach to treatments for nerve pain in your feet.

For non-emergency conditions, simple conservative measures support circulation and relieve nerve tension:
At Medici Orthopaedics & Spine, we emphasize non-surgical, minimally invasive treatments designed to resolve nerve irritation and restore quality of life without relying on heavy medications.
Because numbness blunts pain receptors, patients with peripheral sensory loss face a 15- to 25-fold higher risk of falling compared to those with intact sensation. Daily self-care protects against accidental injuries, pressure ulcers, and balance loss.
Daily Foot and Lower Leg Safety Checklist:
Exercise-induced lower leg numbness is commonly caused by chronic exertional compartment syndrome (CECS), where working muscles expand inside tight fascial compartments, temporarily restricting microvascular blood flow and compressing local nerves. Other frequent causes include over-tightened running shoes compressing dorsal foot nerves, tight calf musculature compressing the common peroneal nerve, or overpronation stressing the tibial nerve. Using dynamic warm-ups, adjusting shoe lacing, improving running cadence, and incorporating lower-leg strengthening often resolves these exercise symptoms.
Vitamin B12 (cobalamin) deficiency is the primary nutritional cause of peripheral numbness. B12 is essential for producing and maintaining the myelin sheath that insulates nerve fibers; its depletion causes progressive nerve demyelination. Deficiencies in vitamin B1 (thiamine), vitamin B6 (pyridoxine), and copper can also cause peripheral neuropathy. Conversely, excessive intake of vitamin B6 supplements (above 100–200 mg daily) can be directly toxic to sensory nerves, triggering paradoxical numbness. Deficiencies are confirmed with simple blood tests and managed with targeted oral or injectable supplementation.
Nerve recovery depends on the underlying cause, the degree of axon loss, and how quickly treatment begins. Peripheral nerves can regenerate at an average rate of roughly 1 millimeter per day if the underlying nerve cell body remains healthy and compression or metabolic stress is resolved. Numbness caused by acute pinched nerves, vitamin B12 deficiency, or early thyroid disorders frequently reverses with timely treatment. While advanced diabetic neuropathy with structural axon loss cannot be completely cured, strict glycemic control, interventional spine care, and focused rehabilitation can halt progression and restore meaningful functional sensation.
Numbness in your calves and feet is not something you should simply push through or ignore. Whether originating from a compressed nerve in the lumbar spine, systemic metabolic changes from diabetes, or restricted arterial blood flow, early medical evaluation is essential to prevent permanent nerve injury, chronic pain, and dangerous balance problems.
Our multidisciplinary team at Medici Orthopaedics & Spine provides personalized care across the greater Atlanta area, including our clinics and surgery centers in Snellville, Kennesaw, Marietta, and Buckhead. If you are struggling with persistent sensory loss, nerve pain, or muscle weakness, explore our comprehensive advanced neuropathy and neuralgia care to schedule your evaluation.
At Medici, you’re more than your MRI.
We take time to hear your story, understand your pain, and create a plan that actually works for you.

Our team delivers specialist care at convenient locations across Metro Atlanta:
Get expert tips on injury recovery, pain relief, joint health, and movement strategies—straight from our Fellowship-Trained team.